Adjustments happen at the post-op visits
A regular exercise plan and a healthy diet are the cornerstones of any weight loss program
What I tell my patients is that BPC-157, if we use it, works best inside a plan: appropriate loading and rehab, real nutritional support, and sometimes alongside regenerative options like PRP injections for the joint or tendon itself
Always consult with a physician before trying new treatments

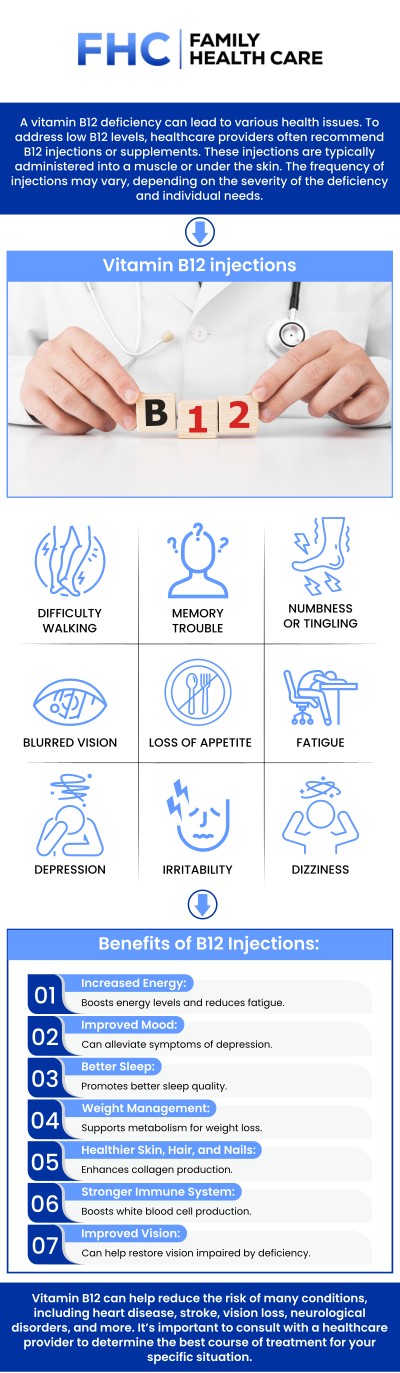
may cause iron-deficiency anemia Nausea and vomiting particularly with stricturing disease/obstruction Urgency and tenesmus with rectal/colonic involvement Weight loss and malnutrition due to malabsorption, food avoidance, elevated metabolic demand Fever with active inflammation, abscess, or fistula Perianal disease fissures, fistulae, skin tags, abscesses Extraintestinal Manifestations Arthropathy peripheral or axial (enteropathic arthritis, M07.6x) Dermatologic: Erythema nodosum (L52), pyoderma gangrenosum, psoriasis (L40.5) Ocular: Uveitis/iritis (H20.01), episcleritis, scleritis Hepatobiliary: Primary sclerosing cholangitis (K73.2), fatty liver, cholelithiasis Metabolic: Osteopenia/osteoporosis (from steroid use and malabsorption), nephrolithiasis Hematologic: Anemia (iron deficiency, B12/folate deficiency, anemia of chronic disease) When a patient with Crohns disease is admitted with significant weight loss, malnutrition, or protein-calorie deficiency , query the provider to specify the degree of malnutrition (mild, moderate, severe protein-calorie malnutrition)