[11] The hypothesis underlying microdosing is that lower doses might provide some metabolic benefit whilst minimising these troublesome symptoms, potentially improving treatment adherence
The reality: Injectables Still set the efficacy ceiling Strongest outcomes + label support Oral drugs Lower efficacy (~1113%) But expand the market significantly Key insight: This is not one oral category Oral semaglutide requires fasting + waiting Orforglipron taken anytime The winner may be the least inconvenient drug, not the most effective The Hidden Problem: Persistence This is the part almost no one talks about: Only ~24.5% of patients remain on therapy at 12 months ~20% switch therapies within a year After stopping: Weight regain 0.8 kg per month Let that sink in
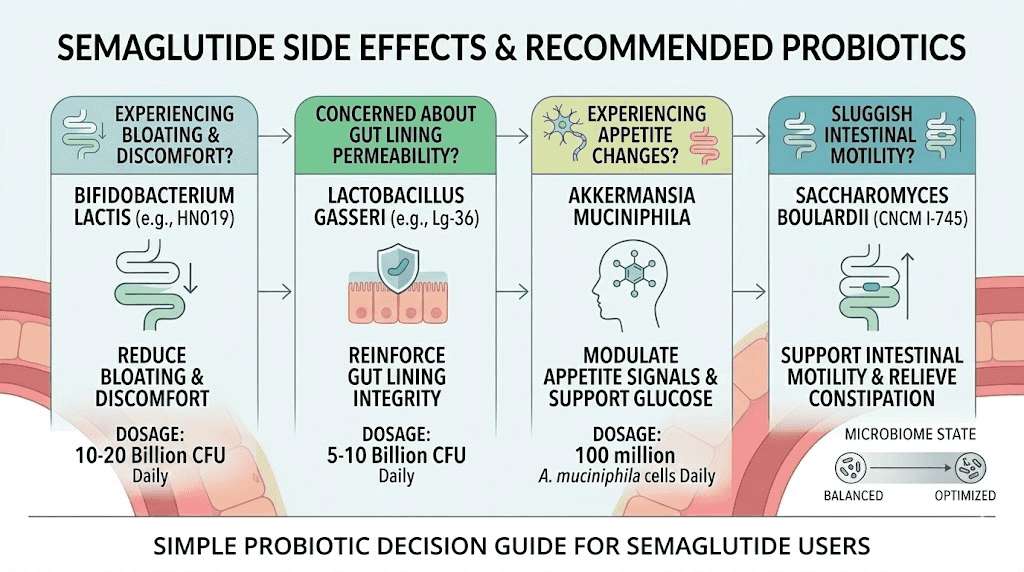
Collectively, these findings signify the multifaceted impact of GLP-1 agonists on gut microbiota composition and metabolic health, offering promising ways for the development of targeted therapeutic interventions for obesity and related metabolic disorders
"Semaglutide proves a game-changer for kidney and heart health in diabetes patients"
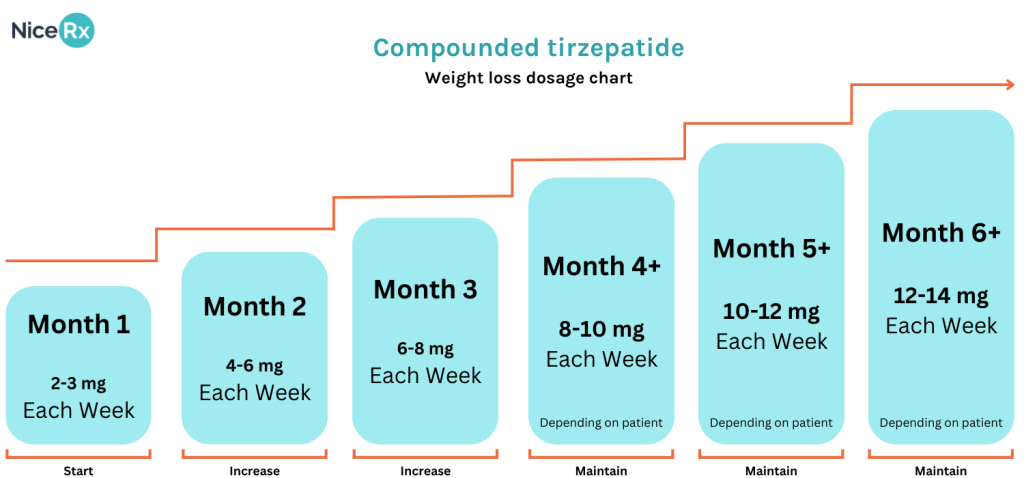
As Blyumin put it, they were given limited use authorizations to compound these drugs that otherwise they shouldnt be able to, because theyre on patent. Now, those shortages have ended, and compounding pharmacies no longer have a legal basis for producing identical copies of GLP-1s